Condor blog
Insights and practical guidance for modern clinical finance teams.

Leading biopharma R&D teams rely on Condor






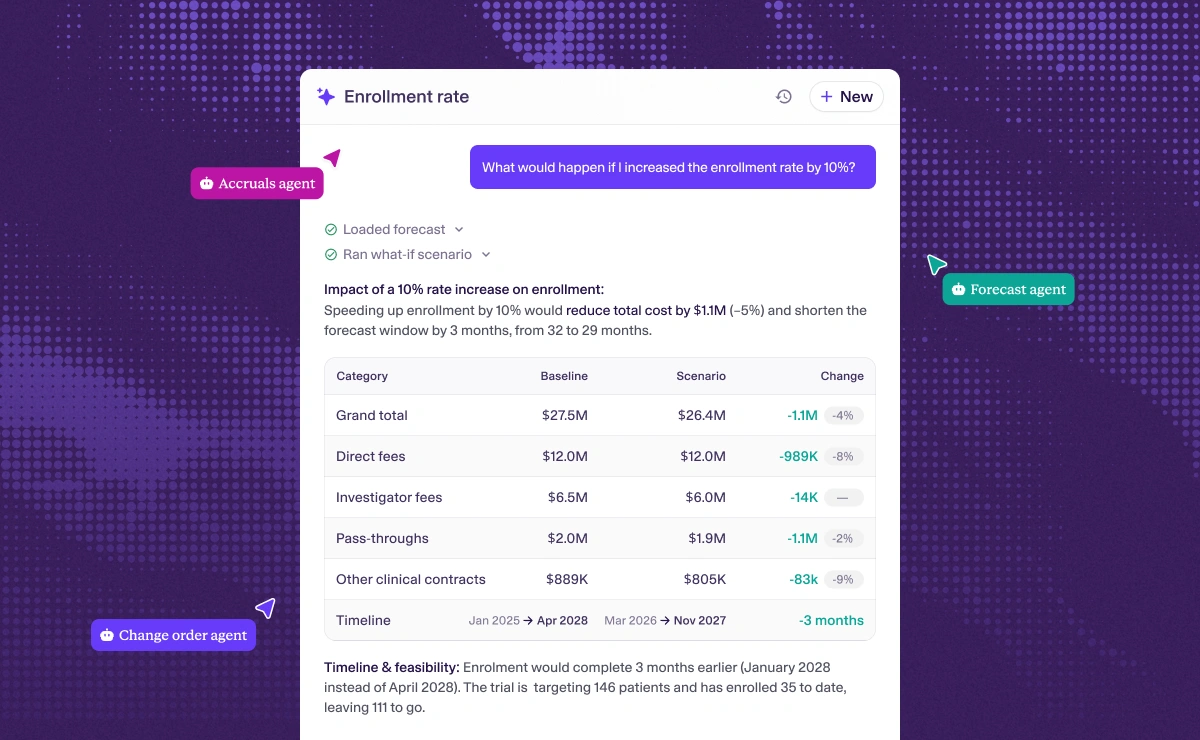
Today we unveiled Condor's Clinical Finance AI Agent — the world's first AI agent purpose-built for biopharma R&D finance.
Ask it why a trial's actuals and forecast diverged, and it reasons across your full budget and forecast history to give you the answer in seconds, not the days it takes to reconcile across your ERP, CTMS, EDC, and a dozen spreadsheets. Ask it what a change in site mix or enrollment timing will cost you, and it runs the scenario and builds the resulting model directly in Condor. It doesn't just surface a number. It gives you the "why," and then it does the work.
This is a big milestone for our company and industry. It's also the moment I've been building toward since the day I started Condor.
The vision I had five years ago
When I founded Condor, I believed the financial machinery underneath every clinical trial could be fully automated, end-to-end, with AI reasoning on top of it.
No more manually managing or outsourcing your finances. The numbers, built by an engine you can trust. Workflows run by AI. The why behind the numbers, uncovered in seconds instead of weeks, while there’s still time to act.
Our new agent is the realization of that vision.
Why it took five years
Building AI that produces numbers you can actually trust is unbelievably hard.
It took building Condor's financial engine first — a deterministic layer that follows defined rules, produces consistent output every time, and is fully auditable. No guessing, no black box, no "the model thinks it's probably right." Every number has to tie back to the clinical activity that actually drove it, because in this industry, a number nobody can defend is a number nobody will use.
It took building a knowledge graph grounded in a clinical and financial ontology we developed over years of work with Big 4 accounting firms — mapping how budgets, vendor contracts, clinical sites, and clinical activity actually connect to each other, across hundreds of studies and therapeutic areas. That ontology is what lets our agents understand a change order or a forecast variance the way a clinical finance team does, instead of the way a generic model guesses.
We built all of that first, five years ago, before there was a market pulling us to do it, because we knew it was the only foundation AI could stand on and still be trusted with a number that ends up in a board deck.
Recently, competitors that built their entire business model around outsourcing clinical finance — putting bodies behind the work instead of automating it — have realized AI is where our industry is headed. They're years behind, so the best they can offer is AI bolted on top of their services model.
Layering AI onto a services model doesn't change what the AI is standing on. If the underlying data was never built for automation — if it was always meant to be assembled by a person — AI on top of it can move faster, but it can't reason with the same grounding as our AI platform. It will take those companies years to build what we have been building for the last five years, because an ontology and a knowledge graph like ours can't be retrofitted. They have to be the starting point.
Why our AI platform matters now, more than ever
For most of the last century, science was the bottleneck in drug development. AI is closing that gap fast, and pipelines are about to fill with more candidates than this industry has ever had to fund at once. Every one of those candidates still has to be forecasted, funded, and managed. Right now, the financial infrastructure doing that job is still, for almost everyone, a spreadsheet.
The bottleneck didn't disappear. It moved from the lab to the ledger. Today, Condor is the only platform built from the ground up to run biopharma R&D finance and operations at the scale AI-driven pipelines are about to demand. Because we built the engine, then the knowledge graph, then the agents, in that order, on purpose.
What comes next
Our Clinical Finance Agent is one of a growing team of agents built on Condor's knowledge graph. Each one, including our forthcoming investigator grant agent, is purpose-built to remove a specific piece of manual work slowing R&D finance and clinical operations teams down.
My vision is here: No more manually managing your finances. The numbers built by our engine. The workflows run by AI. The why behind the numbers uncovered in seconds, not weeks, while there’s still time to act.
This is the start of something big for our industry.
If you want to see the agent for yourself, book a demo.
Recent posts
What We Heard at ABFO 2026: AI Is the Priority — and Many Don’t Know Where to Start

We recently returned from ABFO's National Conference in Philadelphia, where Condor was a proud sponsor and I had the privilege of hosting a panel on how to successfully implement and scale AI in clinical finance. I was joined by Phil Howard, Partner and Integrated Finance Managed Service Leader at EY; Allison Richards, Executive Director of FP&A at BridgeBio; Haiyang Hu, Senior Director of Finance at Addition Therapeutics; and Bobby Fuhrman, Executive Director of Finance at Atrium Therapeutics.
I want to start with a huge thank you to everyone who attended. We had standing room only. Clearly, AI is top of mind for the ABFO community right now.

I wanted to share the slides from our presentation along with a few key takeaways from the session — and from the conversations I had throughout the week. If you’re curious to learn more, join us for our webinar on June 16 from 10-11 am PT. We’ll go deeper on my slides from the session, and discuss where AI is and where it’s heading, how to balance innovation speed with the controls CFOs and auditors expect, and what the highest leverage teams are doing with AI right now.
Everyone Knows They Need AI. Many Don’t Know Where to Start.
The single biggest thing I heard — from the stage, in the hallways, at dinner — was this: I know we need to be doing something with AI. I just don't know what, or how, or who to call first.
One attendee raised his hand during our session and said his entire accounting team was asking for AI licenses and he didn't know where to begin. He's not alone. There's no blueprint yet. And that vacuum is exactly what we want to help fill.
During our panel, we walked through three levels of AI use case maturity:
- Level 1 — Ad hoc LLM use: individuals using ChatGPT or Claude on their own, disconnected from systems or data.
- Level 2 — Pockets of AI use cases: departments starting to deploy AI in specific workflows, but not yet connected across the organization.
- Level 3 — Shared context across the value chain: AI that spans clinical, finance, and operations — with an agentic layer orchestrating insights across the full R&D lifecycle.
When I asked the room how many people were operating at Level 3, nearly no one raised their hand - understandably. The vast majority are still in Levels 1 and trying to figure out how to tackle Level 2.
"AI Might Replace My Job" — A Healthy Fear, and Why I Think It's Actually Good News
The other thing I heard a lot was fear. Not paralyzing fear, but a healthy, motivating anxiety: Am I going to get replaced by this?
I want to be direct: I don't think AI will replace your job. But I do think people who know how to use AI will replace people who don't.
That's not a threat. It's a pattern we've seen play out with every transformational technology. The people who leaned into the change, got curious, and built new skills came out ahead. The ones who waited to be forced into it scrambled to catch up.
Here's how I think about it: one of the core beliefs we shared during our panel is that you can delegate tasks, but you cannot delegate judgment. AI can automate the work — reconciliations, forecasts, accrual support, variance analysis, reporting. But it can’t own accountability. It cannot read the room in a board meeting. It cannot make the call that requires knowing your company's risk tolerance, your pipeline's strategic priorities, or the relationship dynamics with your CRO.
The highest-leverage finance teams will use AI to get the manual work off their plates faster, and then spend more of their time doing the things only humans can do. That's not a smaller role. That's a bigger one.
If your organization hasn't started yet, start now. Buy the license. Let people experiment. The only way to build comfort with AI is to actually use it.
What's Next: A Series to Help You Get Started
At Condor, we believe part of our job is to help the broader R&D finance community navigate this transition. So we're building out a series of resources to help you move from "I need to figure out AI" to "I know exactly what to do next."
Here is the presentation we shared during our ABFO panel:
We've already published:
- Part 1: What AI Is and How It Actually Works — A plain-language primer for finance leaders who want to understand what's actually happening under the hood.
- Part 2: How Our Platform Uses AI to Produce Numbers You Can Trust — How Condor separates its deterministic financial engine from its AI layer, so you get the speed without the risk.
Coming up next: a more tactical post on how to actually get started with AI in your finance function, including the specific steps, the right sequence, and how to build momentum inside your organization.
If you were at ABFO and we connected — thank you! If you have questions about any of this, or want to talk through where your organization is on the AI maturity curve, I'd love to hear from you.
Read the article
Clinical Trial Accruals Are Too Complex for Spreadsheets. Here's What Finance Teams Are Doing Instead.

Clinical trials are not static financial environments. They are extremely change-intensive financial environments. Protocols get amended. Sites open and close. Patient enrollment accelerates or stalls. CROs revise invoices mid-study. Every one of those changes has a financial consequence, and every one of those consequences has to be tracked, reconciled, and reported — accurately, on a deadline, by a team that is almost never large enough.
For a long time, a skilled finance professional with a well-built spreadsheet could absorb that complexity. Not anymore.
Here's what the work actually looks like today. For each active trial, a finance team has to gather CRO reports, pull individual site contracts, compare patient activity data from the clinical team, and manually reconcile everything into a single spreadsheet — ticking and tying across multiple workbooks to arrive at an accrual number they can stand behind. One study, done thoroughly, consumes a full day of multiple people's time. For a company running three to five concurrent trials, quarter-end close can eat nearly a week of the finance team's calendar. Every quarter.
And that's before accounting for errors. Not because the people doing this work are careless — they are not. But because every manual reconciliation is a point of failure. A VLOOKUP pulling from the wrong workbook. A formula that didn't carry through. A CRO invoice that billed multiple patient visits at the wrong rate. These errors exist. They compound. And in many cases, nobody catches them.
Some teams try to solve this by outsourcing the manual work to a software vendor's services team. The logic is understandable, but the risk doesn't transfer with the work. Your name is still on the accruals. Your auditors still come to you, not the vendor, when a number needs to be defended. And you've inserted a human layer between your finance team and the data, which means longer cycles to get answers, to close the books, and to react when a trial's burn rate shifts. The bar for modern R&D finance isn't "faster than a spreadsheet." It's real-time visibility your team controls.
The problem is structural. Clinical trials have gotten too complex, too fast-moving, and too financially consequential for spreadsheets.
There is a better way. At Compass Therapeutics — a lean biotech managing three to five concurrent Phase 1 and Phase 2/3 trials with a two-person finance team — the old process consumed a full day per study, every close. After moving to Condor, that dropped to half a day per study, including reviewer time. Across their active portfolio, they recovered nearly a week of close time every quarter. They caught billing errors that the spreadsheet process never surfaced. They replaced site-level averaging with contract-accurate estimates for every individual site. And they absorbed additional trial volume as their portfolio grew, without adding headcount.
That's what financial infrastructure is supposed to do; it's supposed to scale with the science.
Condor's AI-powered platform automatically connects and unifies clinical, operational, and financial data from the systems and vendors R&D teams already use, eliminating the manual reconciliation layer entirely. Every accrual reflects the actual contracted rate. Every variance is visible. Every number comes with the audit trail that regulators and auditors expect. The manual work doesn't get reassigned. It gets replaced.
Spreadsheets had a good run. But their time has come and gone.
Read the article
How our platform uses AI, and produces numbers you can trust
This is part 2 of a series on How to successfully implement AI. Part 1 covered what AI is. This one covers something more important: Can you trust AI?
I was at an ABFO event in Boston recently, and someone asked: “How do you secure the data and prevent hallucinations?”
AI models don’t “know” things the way a system of record does. They predict. Most of the time, they’re right; sometimes they’re not. Even the best AI gets things wrong sometimes.
So the next question is: How do you build a system where AI errors don’t turn into misstatements and bad guidance?
Most AI tools in finance today plug an LLM directly into workflows and let it generate outputs—numbers, recommendations, summaries—without enough structure underneath.
That’s where most systems go wrong and things break. Because now the same system that can “guess” is also influencing decisions.
How Condor approaches it differently
First: We don’t mix the numbers and the interpretation
We separate two things that should never be mixed: the numbers and the interpretation of the numbers.
1. The numbers (deterministic) - This includes accruals, budget vs. actuals, and forecast rollups. These come from Condor’s financial engine; not AI. They follow defined rules, are consistent, and are auditable. No guessing.
2. The interpretation (AI) - AI sits on top of those numbers, and helps answer questions like:
- What changed?
- What looks off?
- What should I pay attention to?
It finds patterns, flags anomalies, and explains what’s happening. But it does NOT create the numbers. AI can’t corrupt your financials because it never owns them.
Second: humans stay in control
Inside Condor, AI doesn’t take action on its own. Any material output like adjusting a forecast, calculating an accrual, and reconciling a balance requires human review and approval.
AI drafts and you decide. And it’s always clear what’s AI-generated and what’s system-calculated.
Third: security is built in—not bolted on
We treat data security as architecture, not policy.
- Each customer’s data is isolated at the database level
- AI models don’t have direct access to your data
- Only the minimum data needed for a task is shared
- Sensitive data (like patient info) is tightly controlled
- Nothing is stored, reused, or used to train models
Everything is traceable, and every output can be audited.
What this means in practice
The system we’ve built at Condor mitigates AI errors. And when AI is wrong, it gets caught before it matters. That’s why accounting, FP&A, and clinical teams trust Condor to manage over $19B in R&D spend.
Read the article

Best Clinical Trial Accruals Software: A Plain-English Guide for Pharma Finance Teams
If you work in pharma finance, you already know how painful clinical trial accruals can be. Every quarter, your team is hunting down CRO status reports, updating spreadsheet models, chasing vendors for activity data, and trying to make sure the numbers hold up under audit — all while managing a dozen other priorities.
Most pharma companies still do this the hard way: manually, in Excel, with a lot of back-and-forth emails and a lot of crossed fingers. But there's a growing category of software built specifically to fix this problem.
This guide walks through what clinical trial accruals software does, what separates the good tools from the mediocre ones, and how the major vendors compare. Whether you're evaluating options for the first time or trying to replace a clunky legacy setup, this should help you get oriented quickly.
What Are Clinical Trial Accruals — and Why Do They Matter?
Here's the basic idea: when you run a clinical trial, you're paying vendors — CROs, investigator sites, labs, imaging centers, and others — over a long period of time. But those vendors don't always bill you right when the work happens. They might send invoices weeks or months later.
Accruals are how your finance team accounts for money that's been spent (or is owed) even before an invoice shows up. Under GAAP, you have to record expenses when they're incurred — not when you get the bill. For public companies, this is also a SOX requirement, meaning auditors will scrutinize your methodology closely.
In practice, that means your accounting team has to estimate, every single month or quarter, what work has been completed and what it costs. That includes:
- Pulling activity data from your CROs, study sites, and clinical systems (like EDC and IRT platforms)
- Estimating how far along each service category is — direct fees, pass-throughs, investigator grants
- Reconciling those estimates against your contracts, including any change orders or amendments
- Accounting for currency differences if you're running global studies
- Producing journal entries and documentation that auditors can actually follow
- Doing all of this repeatedly, across every active trial, every single period
A single Phase 2 or Phase 3 trial can involve $50M to $500M in vendor spend. Getting accruals wrong in either direction — too high or too low — can misstate your financials and create serious problems at audit time.
The core problem: Clinical trials don't follow clean billing cycles. A CRO might send a monthly summary weeks after the period ends. Sites submit expenses on their own schedule. Protocol changes can shift costs mid-stream. Your finance team has to turn all of that into accurate, period-specific estimates — month after month, for every trial on your plate.
Why Spreadsheets and Manual Processes Don't Cut It Anymore
A lot of pharma finance teams — even ones running late-stage trials — are still doing accruals by hand. They've built elaborate Excel models, they chase CRO contacts for status updates, and they manually reconcile everything before close. It works, sort of. But it has some serious downsides.
1. You're always working with old data
When your accruals are built on delayed invoices or CRO reports that arrive two weeks after the period ends, your numbers are always behind. By the time finance has a complete picture, the trial has moved on. There's no good way to see what's actually happening right now.
2. It eats up your best people's time
Building accruals from scratch every period is slow. Senior accounting staff spend days pulling data, updating models, and chasing down approvals — work that should take hours. That leaves almost no time for anything more strategic.
3. Everything is siloed
Clinical data lives in one system. Contracts and change orders live in another. Financial actuals are in your ERP. None of these talk to each other automatically. So when a protocol amendment happens or a CRO submits a change order, someone on your team has to manually figure out what that means for the financials.
4. Your forecasts go stale fast
A static spreadsheet model can't keep up with what's actually happening in a trial. When enrollment slows down or a vendor changes scope, updating the forecast means rebuilding parts of the model from scratch. By the time you're done, something else has changed. Finance ends up reactive instead of ahead of problems.
По цифрам (в оригинале — три стат-карточки; в блоге можно дать строкой или списком):
- 70–75% — Efficiency gain. Reported by biopharma teams using purpose-built accruals software
- 90%+ — Forecast accuracy. Achievable with automated, data-connected accrual platforms
- >30% — Vendor budget savings. Average per trial with proactive financial management
What Good Clinical Trial Accruals Software Should Actually Do
Not all tools are built the same. Some are purpose-built for pharma accruals. Others are general finance platforms that teams try to adapt. Here are the six things that actually matter when you're evaluating options:
1. It should connect to your clinical data automatically
The whole point of software is to stop manually gathering data. Look for tools that pull directly from the systems your clinical teams already use — Medidata, Veeva, Suvoda, your CTMS — so you're not uploading spreadsheets or waiting on CRO portal exports. If it requires manual data entry, you haven't actually solved the problem.
2. It needs to understand how pharma contracts actually work
Clinical trial contracts are complicated. They have fixed fees, pass-throughs, investigator grants, milestones, and change orders — all in different currencies, across different vendors. Your accruals tool needs to handle all of that natively, not require you to build custom formulas on top of a generic finance platform.
3. Forecasting should be built in, not bolted on
The best tools use the same data for accruals and forecasting. That way, when actuals come in, your rolling forecast updates automatically. You should be able to model "what if enrollment is 20% slower?" or "what if this amendment goes through?" without rebuilding your model from scratch.
4. Auditors need to be able to follow everything
For public companies and pre-IPO biotechs, SOX compliance is a real concern. Every calculation needs to be traceable and documented. Look for tools with full audit trails, role-based access controls, and ideally SOC 1 or SOC 2 certification. Bonus points if the tool was designed with Big 4 audit requirements in mind.
5. It should plug into your existing ERP and finance tools
Accruals end up as journal entries in your general ledger. Your tool needs to integrate cleanly with your ERP — whether that's SAP, Oracle NetSuite, or Sage — so you're not manually rekeying data. Integration with FP&A platforms like Anaplan, Planful, or Adaptive Insights matters too if you're running separate planning workflows.
6. It should scale as you add more trials
A tool that works fine for two trials should still work when you have fifteen. Look for portfolio-level dashboards, multi-entity support, and the ability to handle more volume without proportionally increasing your team's workload.
The Top Clinical Trial Accruals Software Tools
Here's an honest look at the tools pharma finance teams most commonly evaluate — including purpose-built platforms, clinical data systems, ERP tools, and yes, Excel. Some of these are genuinely built for accruals. Others are tools that teams try to stretch to fit the use case. It's worth knowing the difference before you start demo calls.
Condor Software — Purpose-Built · Biopharma
Condor is built specifically for pharma R&D finance — not adapted from a general accounting tool. It automates clinical trial accruals, forecasting, budgeting, and benchmarking. The platform pulls data directly from clinical systems your team already uses (Medidata, Veeva, Suvoda) and connects to your ERP and FP&A tools through its Condor Connect integration layer. The result: your accruals are based on live activity data, not lagging invoices or manual estimates. Finance teams using Condor report closing 60% faster and achieving 90%+ forecast accuracy without growing headcount.
Strengths:
- Native clinical data integrations (EDC, IRT, CTMS)
- Purpose-built accrual engine for biopharma contracts
- 90%+ forecast accuracy, 70–75% efficiency gains
- SOX/SOC-compliant, audit-ready workflows
- Scales from 2 trials to 20+ without headcount growth
- Big 4–trusted outputs
Considerations:
- Focused on biopharma — not a general-purpose finance tool
- Best fit for companies with active clinical programs
Clario (formerly BioClinica) — Enterprise CRO Services
Clario is primarily a clinical services and data capture company — they do endpoint adjudication, eClinical technology, and imaging. Some sponsors using Clario as a CRO get access to spend-tracking portals, but these are built for Clario's own team to manage, not for sponsor-side accounting. If you're looking for a tool to run your own accruals, this isn't it.
Strengths:
- Deep clinical data capabilities
- Established enterprise relationships
Considerations:
- Not a finance/accounting platform
- CRO-side reporting, not sponsor-side accrual automation
- Limited ERP or FP&A integration
Veeva Vault eTMF / CTMS — Clinical Operations Platform
Veeva is the dominant clinical operations platform in pharma — eTMF, CTMS, EDC, and regulatory are all in their suite. It's widely used and holds a lot of the site-level data that feeds into good accrual estimates. But Veeva doesn't calculate your accruals. Think of it as a data source that should connect into a financial platform, not a replacement for one.
Strengths:
- Comprehensive clinical data repository
- Industry-standard in mid-to-large biopharma
- Good API connectivity for downstream finance tools
Considerations:
- Not an accruals or finance platform
- Requires integration with a financial layer for accruals
- High cost and implementation complexity
SAP / Oracle NetSuite / Sage (ERP) — ERP General Ledger
Your ERP is where accruals land as journal entries — it's not where they get calculated. SAP, NetSuite, and Sage are great at what they do, but none of them understand how a CRO contract works. They don't know what investigator fee structures look like or how to handle percent completion across service categories. Companies that try to run clinical accruals directly in their ERP almost always end up layering Excel on top of it anyway — which defeats the purpose.
Strengths:
- System of record for GL and financial reporting
- Strong SOX and audit controls natively
- Already in place at most companies
Considerations:
- No clinical-specific accrual calculation logic
- Requires extensive customization for biopharma use cases
- Acts as destination, not source-of-truth for accruals
Microsoft Excel (Manual Accrual Models) — Spreadsheet-Based
Most pharma finance teams reading this are still using Excel for at least part of their accrual process — and that's fine for one or two trials. But Excel doesn't connect to live clinical data. It has no audit trail. Formulas break. Models get inherited from people who've left the company. And as your trial count grows, the amount of time your team spends maintaining these models grows right along with it. Every other tool on this list should be measured against what it would take to just keep doing things in Excel.
Strengths:
- Universally available, no procurement required
- Fully flexible for any model structure
- Finance teams know it well
Considerations:
- No live data connections — fully manual input
- High error risk; no audit trail
- Does not scale beyond 3–4 concurrent trials
- Cannot support SOX compliance requirements
- Enormous opportunity cost on senior finance staff time
Anaplan / Planful / Adaptive Insights — FP&A / Planning Platforms
Tools like Anaplan, Planful, and Workday Adaptive Insights are widely used by pharma finance for budgeting, planning, and rolling forecasts. Some teams try to build accrual models inside these platforms. The problem: they're not built for clinical contract logic. They don't have native connections to EDC or IRT systems. You'd need to custom-build everything, and it still won't be as accurate as a tool designed specifically for this. They're better used as the downstream home for accrual data than as the engine that produces it.
Strengths:
- Powerful scenario planning and modeling
- Strong financial consolidation capabilities
- Good integration with ERP systems
Considerations:
- Not built for clinical accrual calculation logic
- No native clinical data (EDC, IRT) connectors
- Significant custom build required for R&D use cases
LedgerRun — Clinical Finance
LedgerRun is one of the purpose-built clinical trial finance tools in the market. It handles CRO accruals, contract management, and financial tracking for biopharma. It's generally a good fit for smaller biotech teams looking for something more structured than Excel without a heavy enterprise implementation. Forecasting and benchmarking capabilities are more limited compared to newer platforms, but for teams just starting to move off spreadsheets, it's a reasonable option to evaluate.
Strengths:
- Purpose-built for clinical trial finance
- Relatively fast to implement
- Accessible for smaller biotech teams
Considerations:
- Limited AI/ML-driven capabilities
- Less robust forecasting and benchmarking
- Fewer integrations compared to newer platforms
Medidata (a Dassault Systèmes company) — Clinical Data Platform
Medidata is the industry standard for clinical data capture — EDC (Rave), IRT, and increasingly AI-powered trial analytics. Like Veeva, it holds a huge amount of the patient and site activity data you'd want driving your accrual estimates. But Medidata doesn't do sponsor-side financial accounting. It's the source of the data, not the tool that turns that data into journal entries. You still need something else to close your books.
Strengths:
- Gold standard for clinical data capture
- Extensive data for driving accrual estimates
- Broad industry adoption
Considerations:
- Not a finance or accruals platform
- Expensive; complex implementation
- Finance teams still need a separate accrual system
How They Compare Side by Side
[EMBED: comparison-table]
Questions to Ask Before You Buy
Before you book demos or send out an RFP, get your internal team aligned on what actually matters. The Controller, VP FP&A, and whoever owns clinical finance should all be in the room — they care about different things, and you'll want to surface those differences before a vendor does.
Things you need the tool to do
- Connects directly to our ERP (know which one)
- SOC 1 Type II or SOC 2 Type II certified
- Handles our CRO contract types (fixed-fee, FTE, milestone)
- Automates investigator fee and grant calculations
- Handles multiple currencies and FX automatically
- Full audit trail for every number and journal entry
- Different access levels for accounting, clinical, and FP&A
- We can be up and running in 8–12 weeks
Things that separate the good tools from the great ones
- Live data from EDC/IRT (not just file uploads)
- Rolling forecast uses the same data as accruals
- Can model "what if enrollment slows" scenarios easily
- Can benchmark costs across trials
- Flags variances automatically instead of relying on manual review
- References from companies at a similar stage to ours
- Connects to our FP&A tool (Anaplan, Adaptive, Planful)
- Designed for regulated environments with a validated release process
One thing most teams skip: ask each vendor to walk through a full close cycle using data from a trial that looks like yours. Generic product demos are easy to polish. What you want to see is how the tool handles a messy change order, a mid-period protocol amendment, or a site that's billing late. Bring your Controller and your most complicated CRO contract to that call.
Why Condor Was Built for This
Condor was started because the people who built it had been on the finance side of pharma companies and knew firsthand what a mess clinical trial accruals could be. No existing tool — not the ERP, not the FP&A platform, not the spreadsheet — actually spoke the language of clinical contracts. So they built something that did.
The Condor Platform — three modules that work together as a single financial system for pharma R&D. Each one handles a different piece of the problem — and they share the same underlying data, so nothing falls through the cracks: Connect (Data Integration), Copilot (Workflow Automation), Compass (Intelligence & Benchmarking).
Condor Connect pulls data automatically from the systems your clinical teams already use — Medidata, Veeva, Suvoda, IQVIA, Labcorp, ICON, PPD, Worldwide Clinical Trials, and others — and syncs with your ERP and FP&A platforms. No file uploads, no waiting on CRO portals, no manual reconciliation to get data flowing.
Condor Copilot runs the accrual calculations: applying your contract structures, figuring out percent completion by service category, computing investigator fees and grants, handling currency, building journal entries, and generating the documentation your auditors need to sign off. Finance teams using Copilot report cutting their close time by 60% and reducing the team hours spent on accruals by 70–75%.
Condor Compass takes the data further — connecting clinical and financial information across your full trial portfolio so you can benchmark costs, spot overruns early, and model out long-range scenarios. It's the difference between reporting on what happened and actually steering where things are going.
The platform has been validated by Big 4 auditors and is built with SOX compliance at its core. Customers have gone from managing 2 trials to 10 without adding headcount — and have found more than $5M in savings on individual programs by catching accrual discrepancies and change order exposures before they became problems.
How to Pick the Right Tool
The good news: you have real options now. A few years ago, the honest answer for most pharma finance teams was "use Excel and hope for the best." Today there are tools built specifically to solve this problem, and the case for switching is pretty clear.
If you're running more than two or three active trials — or you know you will be soon — the time and error cost of manual accruals is almost certainly higher than the cost of a purpose-built platform. The finance teams that move first don't just close faster; they get visibility that actually helps with budget decisions and audit prep.
When you evaluate tools, keep the focus on three things: does it connect to your clinical data automatically, does it actually understand how pharma contracts work, and can your auditors follow every number it produces? Everything else is secondary.
The best clinical trial accruals software isn't the one with the longest feature list. It's the one that makes close week less painful, keeps your forecasts accurate, and lets your team spend time on things that actually matter.
Read the article
Introducing our new Advanced Analytics and Dynamic Scenario Suite – Condor’s AI-powered platform now covers the full R&D financial lifecycle

Following closely on the heels of our $24M Series A funding round, today I’m excited to unveil our new Advanced Analytics and Dynamic Scenario Suite — a set of products that give R&D finance teams credible forward-looking intelligence that finance can actually defend in the boardroom, without sacrificing data integrity or waiting on Clinical Operations (ClinOps) to translate trial changes into financial impact.
Biopharma companies can customize views and executive dashboards that are scenario-aware of their forecasting and planning, and traced back all the way to trial-level operational data. You can model enrollment delays or site activations without corrupting actuals, compare forecast versions side-by-side, and synthesize everything into live, shareable dashboards to equip your executive team and peers.
With the addition of the Advanced Analytics and Dynamic Scenario Suite, our AI-powered platform now covers the full R&D financial lifecycle, from automated accruals through forecasting and scenario planning, and all the way to company-wide and executive reporting. R&D teams now have one source of truth from close to strategy.
The suite represents the kind of constant innovation we're driving at Condor. And what we have up next on our product roadmap is even more compelling.
Our product vision is to unite ClinOps and Finance teams via a single source of clinical and financial truth, powered by AI. But not your standard AI. What we’re building at Condor is unique.
ClinOps teams and Finance teams speak different languages. When a CFO needed answers that lived inside clinical operations, or when a clinical team needed to understand a budget decision that nobody had explained to them, the answer is usually to schedule a meeting, wait for the translation, and hope nothing got lost between functions. Meanwhile decisions are paused, programs slow, and surprises surfaced at board meetings.
This isn't a people problem. It's a shared language and understanding problem.
This problem can’t be solved by spreadsheets and services. Some organizations have realized that and are trying to solve the problem using AI. But the way most teams are implementing AI creates a new version of the same problem. You give a generic AI tool a set of rules, you feed it context, and you tell it how your trial works, how your CRO contracts are structured, and how your accruals map to your protocols. For a while, it works! Then the trial changes, the protocol gets amended, a new site opens, and a change order comes in. Now you have to rebuild the rules and feed the AI new context, which takes months. And then six months later, you do it all over again.
Clinical trials are not static. They are arguably the most change-intensive financial environments in any industry. Protocols change, enrollment shifts, and vendors renegotiate. Every change is a new context problem, and generic AI puts that burden on your team, every single time.
Condor is built differently because we started from a different premise. We didn't ask: How do we make AI work on top of your data? We asked: How do we build a system that already understands the relationships between your trial protocols, your site activity, your vendor contracts, and your accounting rules, and updates that understanding automatically as things change?
The answer is a knowledge graph built on a clinical and financial ontology that we developed over years with Big 4 accounting firms. Think of the ontology as the naming system — the semantic layer that defines what everything is and how it relates. The knowledge graph is the navigation system that knows how to move through that structure to find answers. When your protocol changes, the system updates the map. You don't rebuild it or feed it new context; It's already there.
What that unlocks isn't just faster R&D finance. It's something the industry has never had: a genuine translation layer between ClinOps and Finance. Data is unified, current, and explainable—not just to the finance team, but across the broader organization.
When ClinOps and Finance work from the same source of truth, programs move faster. Surprises get caught before they become crises. Go/no-go decisions get made on real data; not on someone's best guess stitched together the night before a board meeting.
Over the course of this year, we’ll introduce a series of AI agents fueled by our clinical and financial ontology and knowledge graph that bring our product vision to life. These agents will function like having multiple clinical finance subject matter experts embedded in your team, surfacing patterns, flagging risks, and bridging context across functions automatically. Not replacing human judgment, rather removing the laborious manual legwork that gets in the way of it.
Stay tuned for more info soon! And if you’re interested in piloting our agents, request a demo here!
Read the article

Definitive Guide: How to Automate Clinical Trial Accruals
Introduction: Why Clinical Trial Accrual Automation Is No Longer Optional
For biopharma finance teams, clinical trial accruals take a lot of time. They are also prone to errors during the R&D close. Analysts spend days chasing CRO invoices. They manually reconcile spreadsheets and build accrual estimates. Those estimates are outdated the moment they are finished. At the end of the month, the team is exhausted and the numbers are still wrong.
The good news is this does not have to be the norm. Automating clinical trial accruals is now within reach for biopharma companies of all sizes — and the results are measurable. Teams that have made the shift report up to a 75% efficiency gain, a 60% faster close cycle, and forecast accuracy that exceeds 90%.
This guide explains what clinical trial accrual automation means. It explains why this challenge is especially difficult in biopharma R&D. It also shows how to approach it step by step. It explains what to look for in a purpose-built solution.
What Are Clinical Trial Accruals?
A clinical trial accrual is the process of recording R&D expenses in the correct accounting period. It applies even if invoices arrive later. Under GAAP and IFRS, biopharma companies must record costs as providers perform the services, not when providers bill them.
In practice, this means estimating how much work a CRO, clinical site, or other vendor finished by each period end. This applies even if no invoice has arrived. The accrual bridges the gap between operational progress and the general ledger.
Clinical trial accruals typically cover:
- CRO pass-through and service fees based on milestone completion and percent-complete estimates
- Investigator fees and site costs tied to patient enrollment and visit activity
- Central lab, imaging, and ancillary vendor costs based on sample volumes and service delivery
- Change orders and protocol amendments that alter original contract values
- Foreign exchange adjustments for multi-currency global studies
Each of these streams requires different data sources, different calculation logic, and different sign-off workflows. Across a portfolio of five or ten active trials, the complexity compounds quickly.
Why Manual Accrual Processes Break Down in Biopharma
Most biopharma finance teams still use ERP systems (SAP, Oracle, NetSuite), Excel files, and email to manage clinical accruals. This approach creates four structural problems that no amount of spreadsheet optimization can solve.
1. Lack of Real-Time Visibility
Accruals calculated from delayed CRO invoices or month-end confirmations are always looking backward. By the time estimates are final, study activity may have shifted. Enrollment may speed up, a site may drop out, or a protocol amendment may change scope. The accrual goes stale before you post it.
2. High Dependency on Manual Processes
Building an accrual model in Excel requires analysts to pull data from many systems. These can include EDC platforms, IRT systems, procurement tools, and contract management systems.
Analysts then copy the data into a workbook, apply formulas, and reconcile results with prior periods. Each handoff introduces the risk of error. Each formula cell is a potential failure point that auditors will want explained.
3. Disconnected Systems and Siloed Data
No single system connects operational trial progress to financial impact. Clinical operations teams track enrollment in one platform; finance tracks budget vs. actuals in another. When a change order is approved, the accrual model does not update automatically.
When a site is activated, the accrual model does not update automatically. Finance hears about it at month-end — if they hear about it at all.
4. Forecast Inaccuracy and Budget Overruns
Static accrual models assume the world stays constant between updates. In clinical development, it never does. Without dynamic, scenario-aware models, finance teams can't accurately project trial spend — and programs run over budget without warning.
"Condor is like night & day from our previous models." — Trishula Therapeutics
The Anatomy of a Modern Clinical Trial Accrual Process
Before you can automate the process, it helps to understand what a well-designed accrual workflow actually looks like. The architecture has three distinct layers.
Layer 1: Data Ingestion
The inputs to any clinical accrual include:
- Contract data — CRO agreements, CTAs, site contracts, and all associated change orders
- Operational assumptions — enrollment timelines, site activation status, percent-complete by service line, and visit completion rates
- Live operational data — EDC data (grant activity), IRT data (site-level enrollment), ERP transaction data, and procurement system records
In a manual process, analysts gather this data by hand. In an automated process, integrations pull this data continuously and map it to the right contract line items.
Layer 2: Calculation and Processing
With the right data, the system uses calculation logic to create accrual estimates for every vendor and service line. This includes:
- Percent-complete calculations for CRO services
- Investigator fee accruals based on visit activity
- Foreign exchange gain/loss calculations for global studies
- Amendment-in-progress reconciliations when change orders are pending
Layer 3: Outputs and Workflow
The outputs of the accrual process feed directly into the financial close. Specifically, the system produces:
- Journal entries ready for ERP posting
- Vendor reconciliation packages for CRO review and sign-off
- SOX/SOC-compliant audit logs and supporting documentation
- Dashboards showing accrual status, budget vs. actual, and trial-level spend
This is also where the guided workflow lives. It includes checklists, role-based approvals, and audit trails. These features make the close defensible to Big 4 auditors.
How to Automate Clinical Trial Accruals: A Step-by-Step Approach
Step 1: Centralize Your Contract Data
The foundation of any accrual automation effort is a unified, structured repository of all your clinical contracts and amendments. This means contract value by service line, milestones, budget categories, and all approved change orders.
Without this foundation, automation is impossible — you can't calculate percent-complete against a contract you haven't structured. Start by extracting and standardizing your CRO agreements, CTAs, and ancillary vendor contracts.
Step 2: Map Operational Data to Financial Categories
Next, create a reliable link between your study work and the records in the general ledger. This requires SMART mapping logic. It translates key milestones, like a patient visit, a lab sample, or site activation. It maps them to matching contract line items and budget categories.
This mapping is where purpose-built clinical finance software creates the most value. Generic ERP systems and accrual tools were not built for the clinical R&D data model.
They need major custom setup, or manual workarounds, to meet these needs.
Step 3: Integrate Your Data Sources
Once your contracts are structured and your mapping logic is in place, you need live data flowing into your accrual models. Integration points typically include:
- EDC platforms (Medidata, Veeva Vault, etc.) for grant and visit data
- IRT systems for site-level enrollment and randomization
- ERP and procurement systems for purchase orders and invoice status
- Contract management systems for approved change orders and amendment status
Automated data ingestion eliminates the manual copy-paste that accounts for a significant portion of close cycle time — and the majority of accrual errors.
Step 4: Automate Calculations and Reconciliations
With structured data flowing in, the system can calculate accruals programmatically. Automated calculations should cover:
- CRO service accruals by percent-complete methodology
- Pass-through cost accruals based on operational data
- Investigator fee calculations by site and patient activity
- Gain/loss calculations for foreign-denominated contracts
- Intelligent reconciliation against prior-period estimates and invoices received
Automation here doesn't mean black-box algorithms. It means repeatable, auditable logic that finance teams can explain to auditors and sign off on confidently.
Step 5: Implement Guided Close Workflows
Automation handles the calculation. Workflow automation handles the coordination. A purpose-built clinical finance system should include:
- A financial close checklist with task assignments and status tracking
- Role-based approvals for accrual review and sign-off
- Integration with accounting systems for journal entry posting
- Audit logs that capture every change, assumption update, and approval
This is where SOX compliance gets built in rather than bolted on. Teams working toward IPO readiness or operating under external audit scrutiny will find that structured workflows reduce the risk of audit findings tied to clinical R&D accruals.
"This [financial close] would never have been possible without Condor." — Intra-Cellular Therapies
Step 6: Build Dynamic Forecasting on Top of Actuals
The final step — and the one that transforms accruals from a compliance function into a strategic tool — is connecting accrual actuals to a forward-looking forecast. When your accrual data is clean, structured, and current, you can build scenario models that project trial spend under different enrollment, amendment, and timeline assumptions.
This closes the loop between the close process and FP&A, giving CFOs and VPs of Finance the real-time visibility they need to manage R&D budgets proactively.
Key Capabilities to Look for in a Clinical Trial Accrual Automation Platform
Not all clinical finance tools are built the same. When evaluating solutions, look for these capabilities:
Purpose-built clinical data model
Generic ERP add-ons and industry-agnostic accrual tools (like Gappify or BlackLine) were not designed with biopharma R&D workflows in mind. A purpose-built platform should natively understand CRO contracts, CTAs, investigator fees, and protocol amendments — without requiring custom configuration to model these structures.
Automated data ingestion
Look for native integrations with EDC platforms, IRT systems, ERP systems, and procurement tools. Manual data imports are a bottleneck and a source of error.
SMART mapping and intelligent reconciliation
The system should automatically map operational data to contract line items, flag variances, and surface amendment-in-progress situations that require reconciliation before the close.
SOX-compliant audit trail
Every calculation, assumption change, and approval should be logged with user, timestamp, and rationale. This is non-negotiable for public companies and Series C+ stage companies preparing for audit.
Unified view for Accounting, FP&A, and Clinical
The best systems give each function a role-specific dashboard built on the same underlying data model — so there's one version of the truth, not three.
Scenario-based forecasting
The platform should allow finance teams to run "what if" models based on enrollment changes, protocol amendments, or timeline shifts — with the accrual layer feeding directly into the forecast.
The Business Case for Clinical Trial Accrual Automation
The ROI on clinical accrual automation compounds quickly. Organizations that have implemented purpose-built automation report:
- 75% efficiency gain on the accrual process itself
- 60% faster financial close cycle
- 90%+ forecast accuracy versus prior-period actuals
- 20% savings per change order through improved reconciliation
- $200K–$10M in vendor budget savings per trial, on average
Beyond the numbers, there is a scaling benefit that spreadsheet-based processes simply cannot provide. One company scaled from 2 active trials to 10 in 120 days — without adding headcount — because their accrual process no longer required a dedicated analyst per study. Another team unlocked over $5M in clinical program savings in a single program through better vendor reconciliation and change order management.
For finance leaders, the business case is straightforward: manual accruals are a constraint on how fast the company can grow. Automation removes that constraint.
Common Objections — and How to Address Them
"We already have an ERP."
ERPs manage transactions. They were not built to calculate clinical trial accruals based on percent-complete methodologies and operational trial data. Most companies using SAP or Oracle for clinical accruals are doing the actual calculation in Excel and posting the result to the ERP. The automation opportunity is in the calculation layer, not the GL.
"Our process works fine for now."
Manual processes work until they don't.
Inflection points often come sooner than teams expect. A new CFO might join. An IPO process might start.
A Series C audit might begin. A pipeline might expand. Building automation early is far less disruptive than adding it under pressure during a close or audit.
"We don't have the IT resources for implementation."
Purpose-built clinical finance platforms support fast implementations with minimal IT burden. The heavy lifting is in the clinical data model and integration layer. It comes pre-built, not from custom development.
Conclusion: From Reactive Close to Proactive Control
Automating clinical trial accruals is not just an efficiency play. It is the foundation for transforming clinical finance from a reactive, backward-looking function into a proactive one.
Finance teams gain real-time visibility into trial spend. They also get accurate forecasts. They can scale as the pipeline grows.
Centralize your contract data. Link your key operational data sources. Move calculations out of spreadsheets and into a purpose-built system. The result is a faster close, cleaner audits, and a finance team that keeps up with complex biopharma R&D.
Condor is the Financial Cloud for Pharma R&D — purpose-built to automate clinical trial accruals, forecasting, budgeting, and benchmarking. To learn how leading biopharma finance teams are automating their R&D accruals with Condor, request a demo at condorsoftware.com.
Read the article